


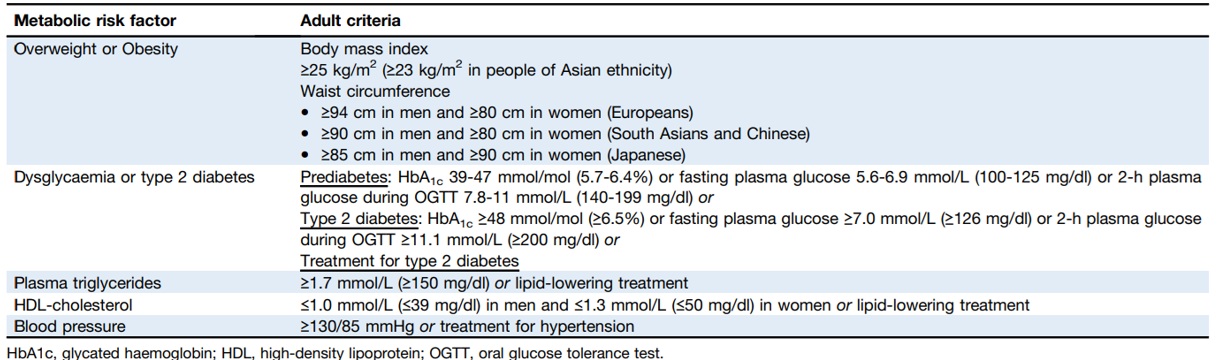
MASLD (previously known as Non-alcoholic fatty liver disease, NAFLD) is a condition in which the excess amount of fat builds up inside the liver. MASLD is caused by the presence of one or more cardiometabolic risk factor(s) in the absence of excess alcohol intake
Spectrum of MASLD
MASLD develops in 4 main stages:
- Steatosis – a build-up of fat in the liver cells that may only be diagnosed during tests carried out for another reason
- Metabolic dysfunction-associated steatohepatitis (MASH, formally NASH) – a more serious form of NAFLD, where the liver has become inflamed
- Fibrosis – where persistent inflammation causes scar tissue around the liver and nearby blood vessels, but the liver is still able to function normally
- Cirrhosis – the most severe stage, occurring after years of inflammation, which can lead to liver failure. Ultimately this can result in MASH-related hepatocellular carcinoma (HCC)
It can take years for fibrosis or cirrhosis to develop. It’s important to make lifestyle changes to prevent the condition getting worse.
Cardiometabolic risk factors in definition of MASLD
Referral Pathway For MASLD

FIB-4 Calculation
Fibrosis-4 (FIB-4) Index for Liver Fibrosis – non-invasive estimate of liver scarring.(calculate here)
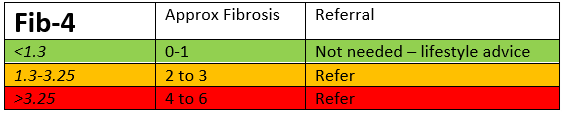
With regards to referrals and Fib-4:
- cut offs above refer to ≤65 years
- over 65, the cut off for referral is 2.0
- under 35s, Fib-4 is not especially reliable
Of note, gastro generally avoid liver biopsies unless:
- patients might be eligible for a trial (e.g. patients who have higher fibrosis scores)
- features to suggest an alternate diagnosis such as a positive autoimmune markers
- non-invasive fibrosis markers such as Fib-4 or fibroscan/serum ELF test do not corroborate each other
Suggested Interventions for those with MASLD
- 7-10% weight loss recommendation. Those at risk should be considered for structured weight loss programs or bariatric surgery as per NICE guideline. Patients can self-refer to healthy lifestyles Coventry NHS health programme Home HLS Coventry (https://hlscoventry.org/ ) or better health – https://www.nhs.uk/better-health/
- Mediterranean diet can be recommended, as can limit consumption of fructose-enriched beverages
- Regardless of weight loss exercise is advised to reduce associated cardiovascular risk – aim for 150 minutes of moderate intensity/week
- Q-Risk score calculation
- Diabetes care
- Alcohol and smoking cessation advice
Follow-up
MASLD is now the leading cause of chronic liver disease in the world.
Many MASLD patients will have little progression in their disease, however a subset will progress to liver fibrosis and cirrhosis.
Patients with MASLD should have their fibrosis scores trended over time to evaluate for progression or stabilisation.
The FIB-4 score can reduce liver biopsies in those patients predicted to have a low risk of fibrosis by their score
Depending on score and local prevalence of advanced fibrosis, the score can be used to reliably predict (with high 80-low 90% accuracy) which patients are unlikely to have cellular evidence of fibrosis on biopsy.
FIB-4 was developed to correlate with Ishak levels of fibrosis (by biopsy) with 3 levels:
- 0-2 (mild fibrosis)
- 3-4 (moderate fibrosis)
- 5-6 (severe fibrosis/cirrhosis)
While liver biopsy is the gold standard for the diagnosis of liver fibrosis, it is not ideal; biopsy only evaluates a minute portion of the liver itself, so sampling errors can occur. Liver biopsy also comes with substantial morbidity.
 For review soon
 Awaiting review
 Invalid notification
 Coventry
 Rugby & South Warwickshire
 North Warwickshire
 South Warwickshire
Leave feedback
You must be logged in to post a comment.